



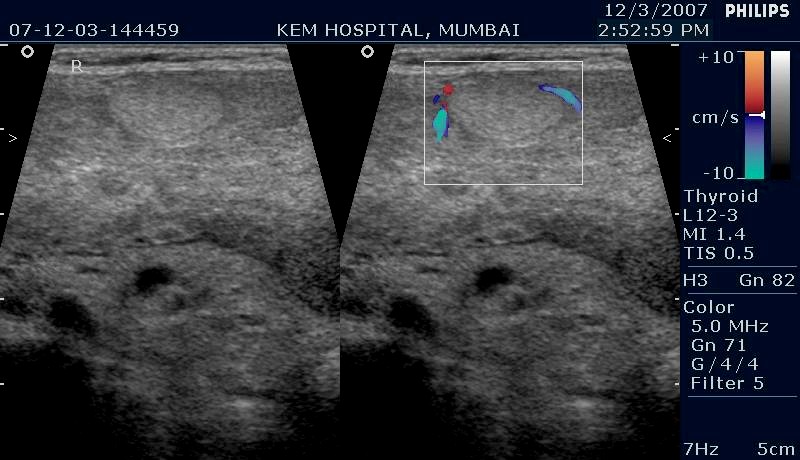
In the general population, thyroid nodules are found in 5% by palpation and in 50% by ultrasonography (US).
Thyroid nodules are more common in women than in men.
The clinical importance of thyroid nodules, besides the infrequent local compressive symptoms or thyroid dysfunction, is primarily the possibility of thyroid cancer, which occurs in about 5% of all thyroid nodules regardless of their size .
Causes of thyroid nodules-
1) Benign
Colloid nodule
Hashimoto thyroiditis
Simple or hemorrhagic cyst
Follicular adenoma
Subacute thyroiditis
Hashimoto thyroiditis
Simple or hemorrhagic cyst
Follicular adenoma
Subacute thyroiditis
2)Malignant
Primary
1,Follicular cell-derived carcinoma:
PTC, follicular thyroidcarcinoma, anaplastic thyroid carcinoma
2)C-cell–derived carcinoma:
MTC
3)Thyroid lymphoma
4)Secondary
5)Metastatic carcinoma
USG FINDING IN MULTINODULAR GOITRE-
Gray scale ultra sound –
Gray scale ultra sound –
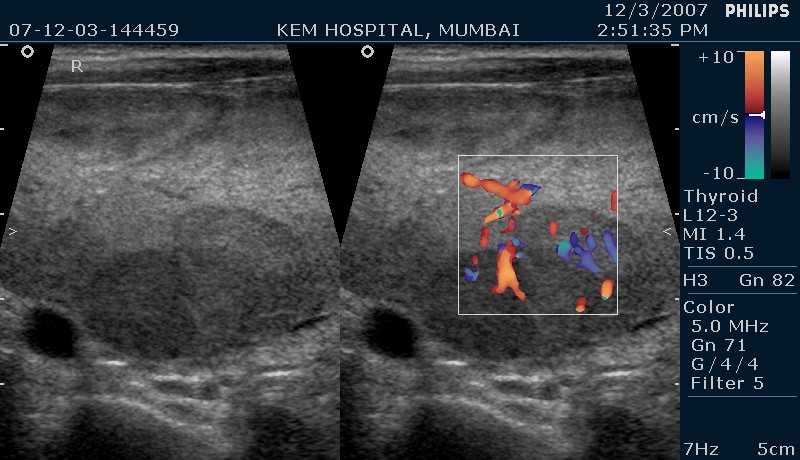
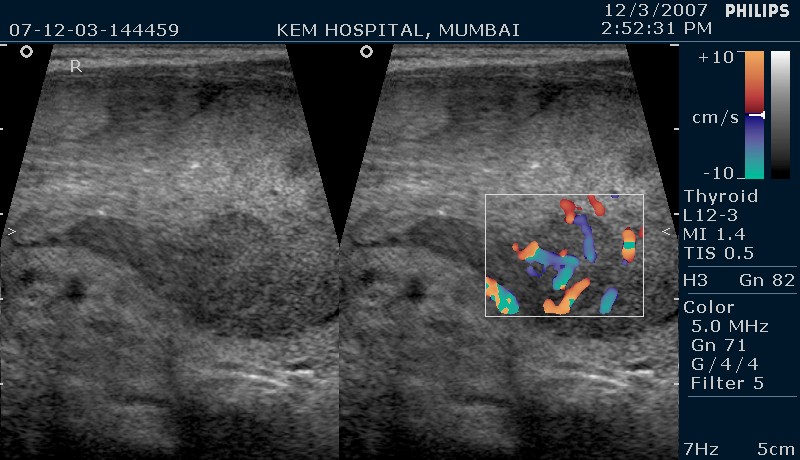
1)multiplicity of nodules and b/l diffuse involvement.
2)solid nodules are often isoechoic with small proportion being hypoechoic.(5%)
3)despite being unencapsulated ,nodules sharply defined with halo,which composed of adjacent vessels and compressed thyroid.
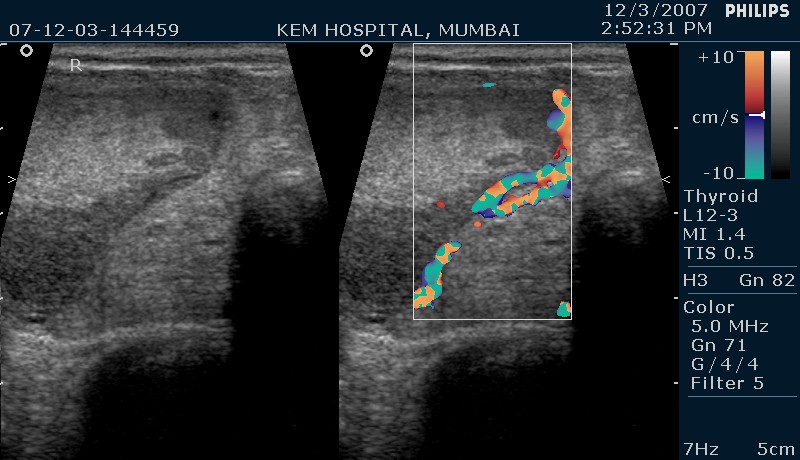
4)heterogeneous internal echo pattern with internal debris , septa , solid cystic portion., solid portion often represent blood clot
5) dense shadowing calcification .
6)nodules showing comettail artifact highly s/o colloid nodules .
7)cystic component due to hemorrhage or colloid within nodule .
8)colour dopper –peripheral vascularity> intranodular vascularity.
Increased risk of malignancy in thyroid nodule-
• History of childhood head/neck irradiation
• Family history of PTC, MTC, or multiple endocrine neoplasia type 2 (MEN2)
• Age <20 or >70 years
• Male sex
• Enlarging nodule
• Abnormal cervical adenopathy
• Fixed nodule
• Vocal cord paralysis
ULTRASOUND PREDICTION OF MALIGNANCY-
1) SOLITARY VERSUS MULTIPLE NODULES-
The risk of cancer is not significantly higher for solitary nodules than for glands with several nodules, whether the nodules are palpable or impalpable. In glands with multiple nodules, selection for FNAC should be based on US features rather than on size or clinically “dominant†nodules.
1) In multinodular thyroid glands, the cytologic sampling should be focused on lesions characterized by suspicious US features rather than on larger nodules.
2)If two or more thyroid nodules >1–1.5 cm are present, those who have a suspicious US appearance should be aspirated preferentially.
3) In patients who have multiple discreet nodules, the selection should be based primarily on US characteristics rather than nodule size.
2) Size -.
US-FNAC should be considered for nodules smaller than 10 mm if associated with punctate microcalcifications, if a history of neck irradiation is present, or in a young patient .
Because some microcarcinomas can have aggressive clinical behavior, early diagnosis by FNA of a small (<10 mm) PTC followed by immediate thyroidectomy may not only decrease morbidity but also be curative.
3) Ultrasound features and color Doppler findings-
The specificity of US features for diagnosing cancer varies
a) from 85% to 95% for microcalcifications (small intranodular punctate hyperechoic spots, with scanty or no posterior acoustic shadowing) .
b) from 83% to 85% for irregular or indistinct nodule margins,
c) and about 81% for chaotic appearance of intranodular vascular images.
d) Color Doppler US evaluates nodule vascularity. The assumption is that hypervascularity with chaotic arrangement of blood vessels favors malignancy, whereas peripheral flow indicates a benign nodule. .
Hence presence of at least two suspicious sonographic criteria reliably identifies 85% to 93% of thyroid gland neoplastic lesions.
4) Extracapsular growth
Hypoechoic nodules with irregular borders, extension beyond the thyroid capsule, invasion into perithyroid muscles, and infiltration of the recurrent laryngeal nerve are sonographic features that warrant cytologic evaluation .
5)Complex or cystic lesions
Complex thyroid nodules have solid and cystic components, often with a dominant cystic part, and are frequently benign. These lesions are common, frequently smaller than 3 or 4 cm in diameter, and asymptomatic. US-FNA is necessary to document the morphology because some PTCs may be cystic .
6)Nodule shape
A rounded appearance or a “more tall (anteroposterior) than wide (transverse)†shape of the nodule and a “marked hypoechogenicity†of a solid lesion (hypoechoic even compared with the cervical muscles) are newly described US patterns suggestive of malignancy .
7)Suspicious cervical adenopathy
Enlarged cervical lymph nodes that have a rounded appearance by US, no hilus, cystic changes, microcalcifications, or chaotic hypervascularity have a high probability for malignancy